


Goodbye to back pain
Back pain limits far more than movement: it affects your sleep, your energy and your daily life.
At Clínica FISARE we treat spinal problems with a rigorous clinical approach, focused on the real source of the pain and not only on its symptoms.
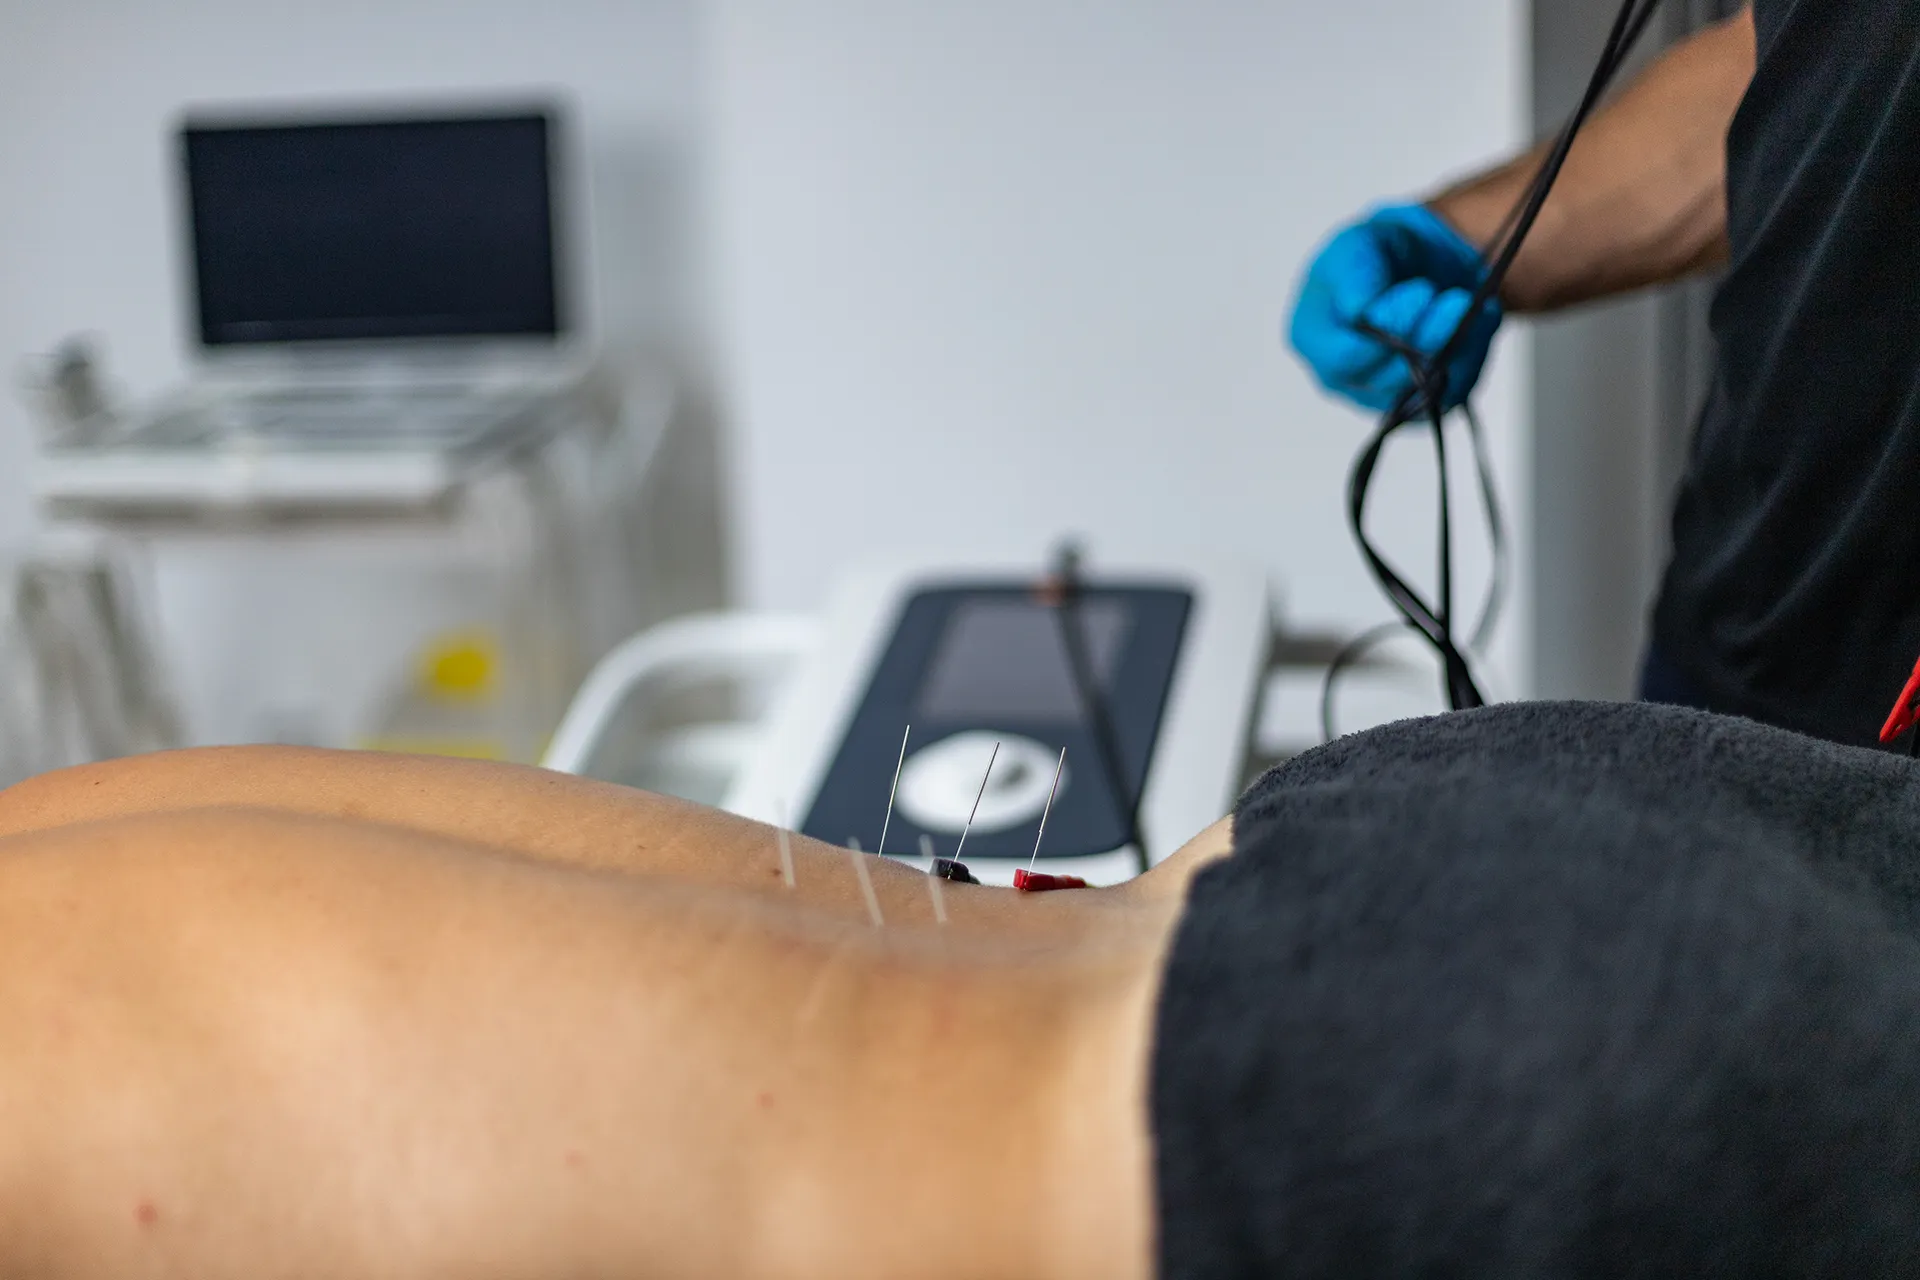
We combine manual therapy, invasive neuraxial physiotherapy, ultrasound and therapeutic exercise to help you restore mobility, reduce pain and prevent relapses. All within a treatment plan that is clear, measurable and adapted to you alone.
English spoken. No medical referral needed to book.

HOW WE WORK
Regain confidence in your body
Step 1
Full assessment
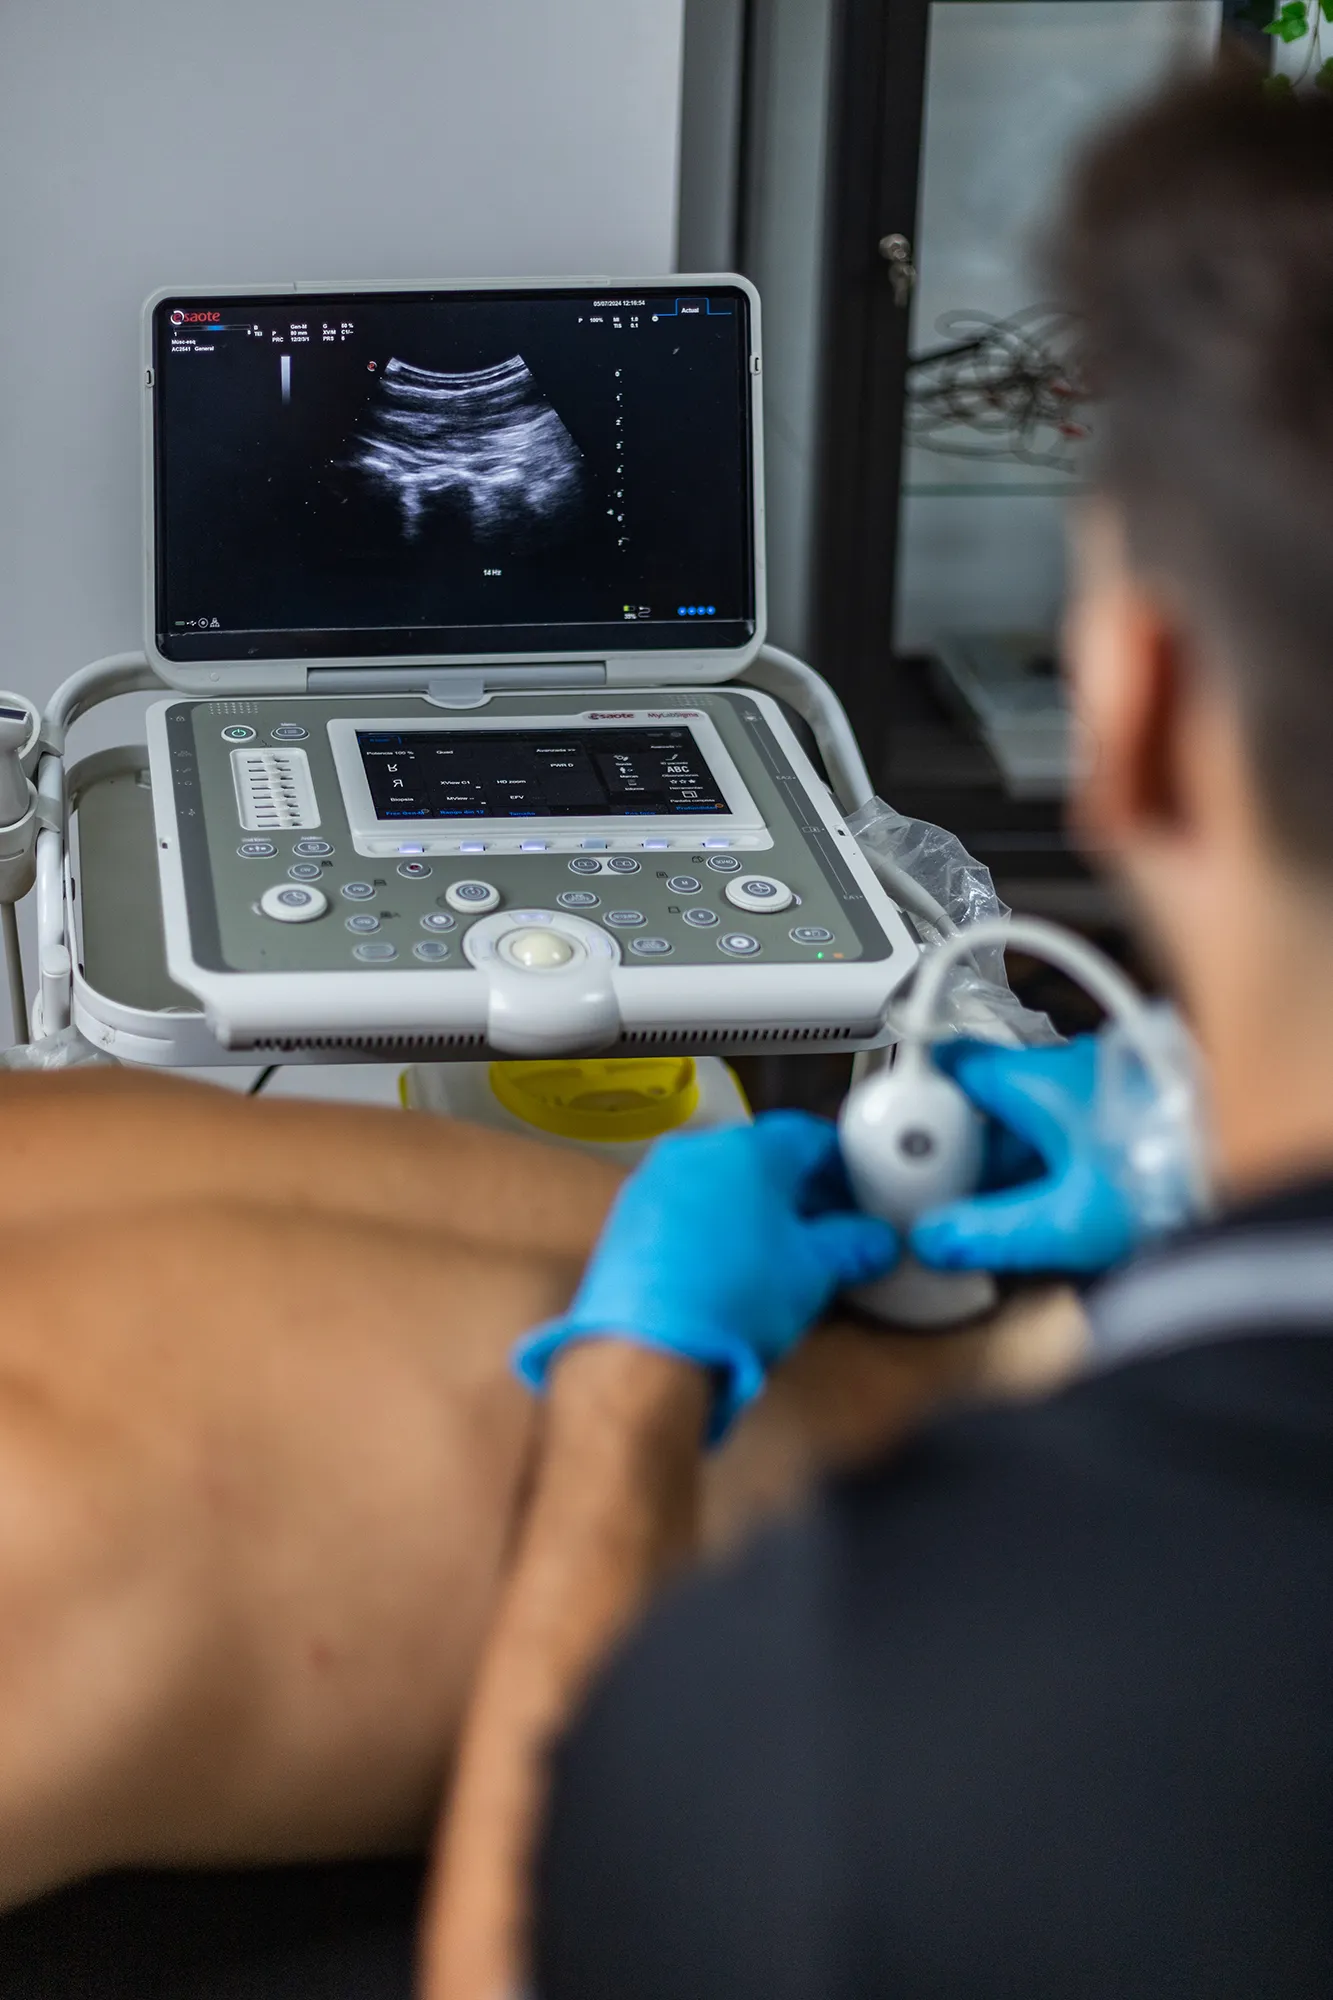
Using ultrasound and specific testing, we analyse the real cause of your pain.
Step 2
Treatment plan
We design a tailored programme combining manual techniques, invasive techniques and exercise.
Step 3
Advanced therapy
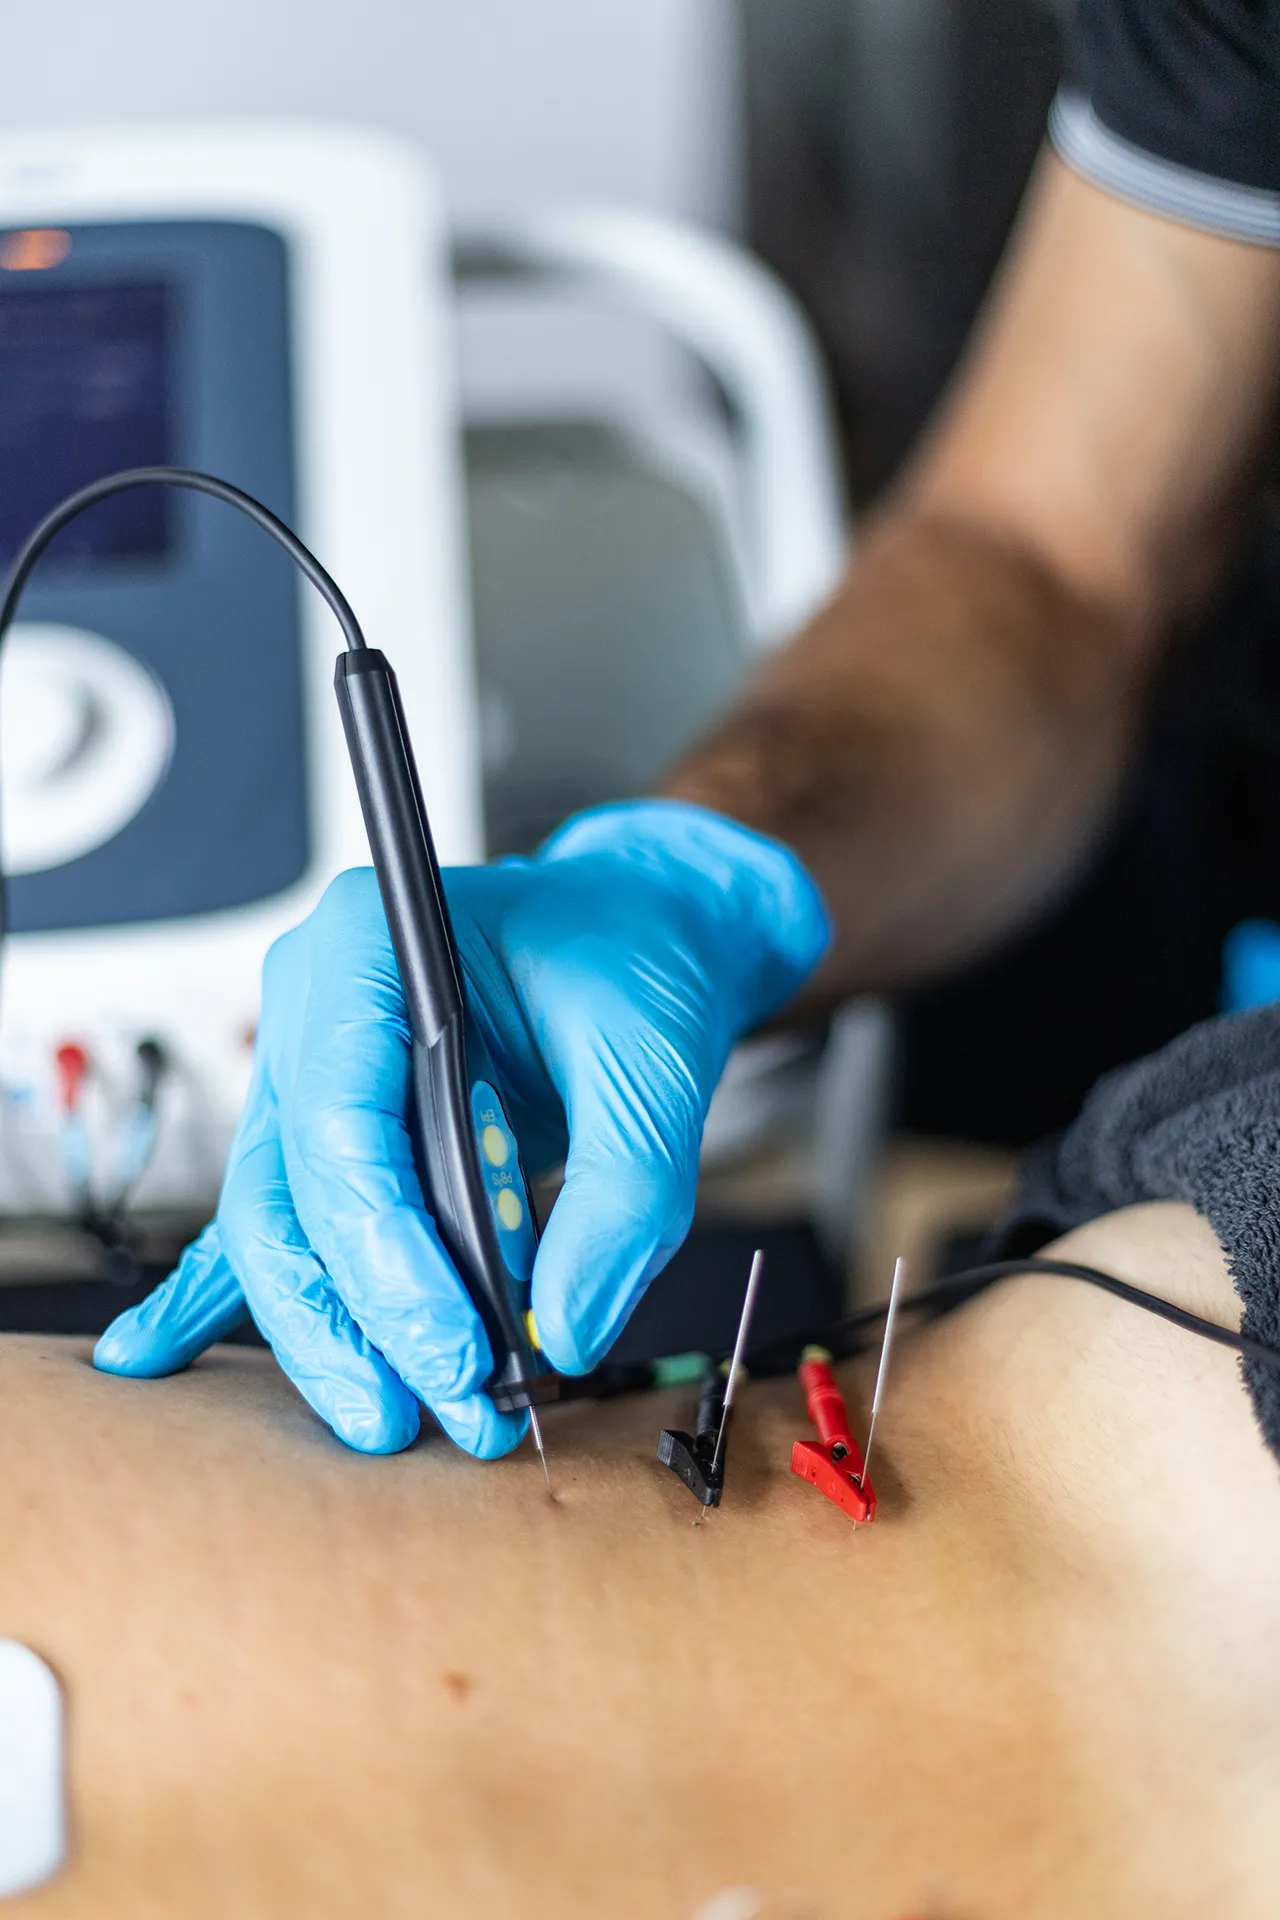
We apply tools such as neuromodulation, radiofrequency and EPI to speed up your recovery.
Final step
Follow-up
We guide you through an exercise plan and review appointments to keep your back strong and pain-free.
Spinal Physiotherapy
Why choose us
At Clínica FISARE we don’t offer generic solutions: every patient gets a unique plan, adapted to their case. Our combination of precise assessment, advanced technology and close follow-up has made us a reference point in the treatment of back pain in Manacor.
Most importantly, you’ll never be on your own. We’re with you step by step, answering your questions and adjusting the treatment as you progress.
Testimonials
What people who have recovered tell us
Publicado en Google
FAQ
What people ask us most about back pain
How long does low back pain last?
Most episodes of acute low back pain improve substantially within 4–6 weeks, and many of them sooner.
What isn’t normal is for pain to become chronic without anyone having assessed why: when pain persists beyond 12 weeks the approach has to change, because we’re no longer treating just an irritated tissue but a system that has learnt to hurt. That’s where a thorough assessment makes the difference between getting better and stumbling along.
I have had an MRI and it shows herniations or wear — is that what is hurting?
Not necessarily, and this is one of the most common misunderstandings we see. Studies in people with no pain at all show that degenerative findings — protrusions, disc dehydration, facet arthrosis — are extraordinarily common and increase with age: many people in their 40s or 50s have herniations on an MRI and have no idea.
That doesn’t mean your scan is irrelevant; it means what’s seen has to be correlated with what we find on examination. We treat people, not reports.
Should I rest or should I move?
Move, with few exceptions. Current clinical practice guidelines agree in advising against bed rest for low back pain: it delays recovery, causes loss of strength and increases fear of movement.
It’s a different matter that in the first few days you may need to adapt what you do and how you do it. Our job isn’t to tell you to rest — it’s to help you keep moving in a way your back can tolerate today, and then widen that margin.
I have a disc herniation. Do I need surgery?
That decision is a medical one and belongs to your orthopaedic surgeon or neurosurgeon, not to us.
What we can tell you is what the evidence shows: most symptomatic disc herniations progress favourably with conservative treatment, and many resorb spontaneously over time. Surgery is reserved above all for cases with progressive neurological deficit, cauda equina syndrome, or disabling pain that doesn’t respond over a reasonable period of treatment. Our role is to support you through that conservative period and give you objective information so you can decide together with your doctor.
What is sciatica and how long does it take to go away?
«Sciatica» is the popular name for pain that radiates down the leg along the path of a nerve root, usually because that root is compressed or irritated.
It tends to be more troublesome and slower than simple low back pain: the usual timeframes run from several weeks to a few months, with progressive improvement. What matters isn’t only that the pain settles, but that you recover strength and sensation if you’d lost them. If you notice clear loss of strength in your foot or leg, tell your doctor.
What is invasive neuraxial physiotherapy?
It’s the application of needle techniques, guided by ultrasound, to structures related to the nervous system and the deep musculature of the spine, with the aim of modulating pain and improving tolerance to movement.
It doesn’t replace exercise: it’s a tool to open a window of less pain in which we can work. Like any invasive technique, it requires prior assessment and isn’t indicated in every case.
I have seen back exercises online — are they any use to me?
Some are and some could make you worse, and the problem is that nobody can tell from a screen what your case is. The same exercise that relieves one person with sensitisation-driven pain can irritate another with an active radiculopathy. The dose — how often, with how much load, with what progression — matters as much as the exercise itself.
If you’re going to do something on your own, make it walking and staying active; for the rest, better to have someone assess what your back needs right now.
When should I be concerned and see a doctor?
There are signs that require medical assessment rather than physiotherapy: loss of bladder or bowel control, or numbness in the genital and perineal area — this is an immediate medical emergency — progressive loss of strength in a leg, fever accompanying back pain, unexplained weight loss, pain that doesn’t ease at all at night or with a change of position, or pain appearing after significant trauma.
We screen for these signs in our assessment, and if any appear we refer you without treating you.
Ready to leave back pain behind?
Book your appointment today and start a treatment that isn’t based on sessions, but on a plan to get you living without pain again.

